Premature ejaculation

Stop rushing. Start lasting.

Clinically proven treatment, prescribed by a UK-registered clinician.

From £14.30 / month

Based on EMLA. Your price depends on the treatment a clinician prescribes.

  • Two routes — a tablet or a cream
  • From 0.9 to 3.3 minutes on average in trials1
  • Delivered free, in plain packaging

Takes 4 minutes · If a clinician doesn’t prescribe, you’re refunded in full

A couple relaxed and close together in bed
Medication options

More than one route.

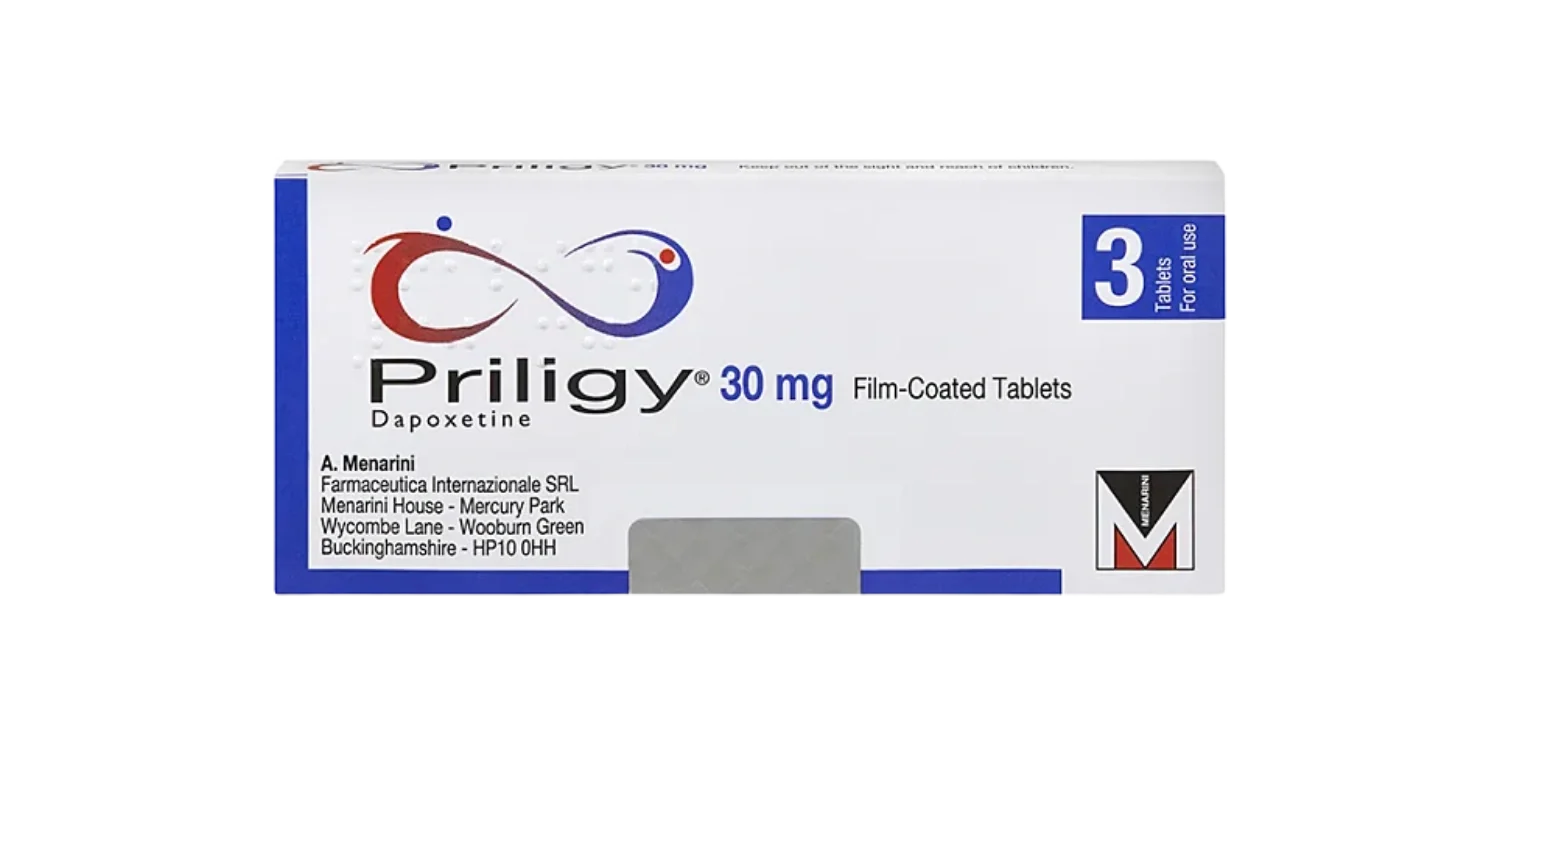
Priligy tablets

Priligy dapoxetine

From £27.98 / month

1 to 3 hours before sex

A prescription tablet for premature ejaculation, and the option most prescribers start with.

  • Taken 1 to 3 hours before sex
  • A tablet, not a cream
  • Reviewed by a registered clinician
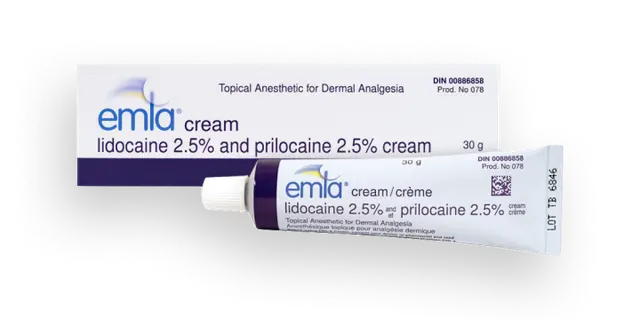
EMLA cream

EMLA lidocaine and prilocaine

From £14.30 / month

Applied before sex

A numbing cream rather than a tablet.

  • A cream applied before sex
  • No tablet to take
  • Reviewed by a registered clinician

There isn’t a single “best” treatment, the right one depends on you. Here’s what a clinician may consider, though the final choice, and whether treatment is suitable at all, is always theirs to make with you.

The whole programme

Your treatment journey

1
Starting an online assessment
Before you start

Your assessment

  • A four-minute online assessment
  • Prescribed only if it's right for you
  • They check what else may be driving it

2
Starting treatment at home
First few times

Getting started

  • The option and dose your clinician sets
  • Finding your timing takes a few goes
  • Free delivery, in plain packaging
3
Finding the right option and timing
Weeks to months

Finding what works

  • Dose and timing reviewed as you go
  • A clinician can switch the option
  • Technique and pacing help too
4
Ongoing support from the care team
Ongoing

Ongoing support

  • Regular check-ins, support when things change
  • Cancel anytime, month to month
  • A care team a message away
The people behind your care

Clinicians, not chatbots.

Dr. Feroz Zafar, Medical Director at Manova

Medical Director

GMC 7266874
Naeem Teni, Clinical Lead at Manova

Clinical Lead

GPhC 2215591
Saiyma Zafar, Head of Clinical Operations at Manova

Head of Clinical Operations

GPhC 2052120

The bit that isn't marketing.

Placeholder layout - replace with verified patient reviews before launch

Placeholder text. A short review sits here, about two lines, so you can see how the card looks at its smallest.

–Reviewer namePremature ejaculation · month

Placeholder text. This card carries a medium-length review, roughly four lines of body copy, which shows how the card grows and where the name settles underneath it.

–Reviewer namePremature ejaculation · month

Placeholder text. A longer review runs to about six lines, which is roughly the most this layout carries comfortably before the row starts to look unbalanced against the two cards beside it.

–Reviewer namePremature ejaculation · month
FAQs

Asked more often than you'd think.

There are published numbers for this, so here they are rather than a vague reassurance.

Across the dapoxetine phase 3 trials, average time to ejaculation started at 0.9 minutes. After twelve weeks it was 3.6 minutes on the 60 mg dose, 3.1 minutes on 30 mg, and 1.9 minutes on placebo.

For the lidocaine/prilocaine spray, the two main studies recorded averages of 2.6 minutes and 3.8 minutes against 0.8 and 1.1 minutes on placebo.

Note how much the placebo groups improved too — a reminder that expectation plays a real part here. And “longer” is not automatically the goal: for most couples the thing that genuinely improves is the anxiety surrounding it.

Faster than most treatments — this is not something you build up over weeks. Dapoxetine is taken one to three hours before sex and works that same occasion. A topical spray goes on about five minutes beforehand.

So you will know quite quickly whether it suits you. Which also means it is worth trying on more than one occasion before deciding, since a single attempt tells you as much about the evening as the treatment.

It should not — these treatments act on ejaculation, not erection.

There is one caveat with a topical spray: too much of it, or leaving it on too long, can dull sensation more than you want and occasionally make an erection harder to maintain. Washing off the excess before sex is part of the instructions for a reason, and it is the step people skip.

Often, yes — and it is far more common than people assume. The two frequently coexist, and sometimes premature ejaculation is downstream of worrying about losing an erection rather than a separate problem.

Whether they can be treated together depends on the specific combination and your health, so raise it in your assessment rather than ordering both separately and hoping they get along.

That the medicine is licensed for a different condition, but there’s enough evidence for a clinician to prescribe it for this one. It’s normal, legal and common in medicine, and your clinician should tell you when they’re doing it, and why.
Every case is read by a registered clinician. They can and do say no when treatment isn’t appropriate, that’s the point of having a clinician rather than a checkout button.
Then you’re not charged. The clinician might suggest a different option, ask for more information, or refer you back to your GP. We’d rather lose a sale than push the wrong treatment.

References

  1. Pryor JL, Althof SE, Steidle C, et al. Efficacy and tolerability of dapoxetine in treatment of premature ejaculation: an integrated analysis of two double-blind, randomised controlled trials. The Lancet, 2006;368(9539):929–937 — DOI: 10.1016/S0140-6736(06)69373-2. Integrated analysis of two 12-week randomised, double-blind, placebo-controlled trials (n=2,614). Figures are mean intravaginal ejaculatory latency time at study endpoint. Results are from a clinical trial population; individual results will vary.