

Key takeaways
- The UK now has two injectable GLP-1 based medicines licensed for weight management and two oral ones.
- Injections are weekly; tablets are daily. Oral semaglutide needs an 8-hour fast, orforglipron does not.
- Trial weight-loss averages differ, but the trials were run in different populations and are not head-to-head comparisons.
- All of them are prescription-only, and none of the newer options is routinely available on the NHS.
Two years ago there was effectively one conversation to have about weight-management medicines in the UK. Now there are four licensed options working on the GLP-1 system, in two different delivery formats, plus an older tablet that works in a completely different way.
This page is a factual comparison. It is information about prescription-only medicines, not advice about which — if any — is right for you.
What is licensed in the UK
| Medicine | Form | How often | Notes |
|---|---|---|---|
| Tirzepatide (Mounjaro) | Injection | Weekly | Dual GIP/GLP-1 agonist. Max 15 mg [3] |
| Semaglutide (Wegovy) | Injection | Weekly | Max dose raised to 7.2 mg in 2026 [4] |
| Semaglutide (Wegovy) | Tablet | Daily | 25 mg; requires an 8-hour fast [2] |
| Orforglipron (Foundayo) | Tablet | Daily | No food or water restrictions [1] |
| Liraglutide (Saxenda) | Injection | Daily | Older GLP-1; max 3 mg [5] |
| Orlistat (Xenical, Alli) | Capsule | With meals | Blocks fat absorption, not a GLP-1 [6] |
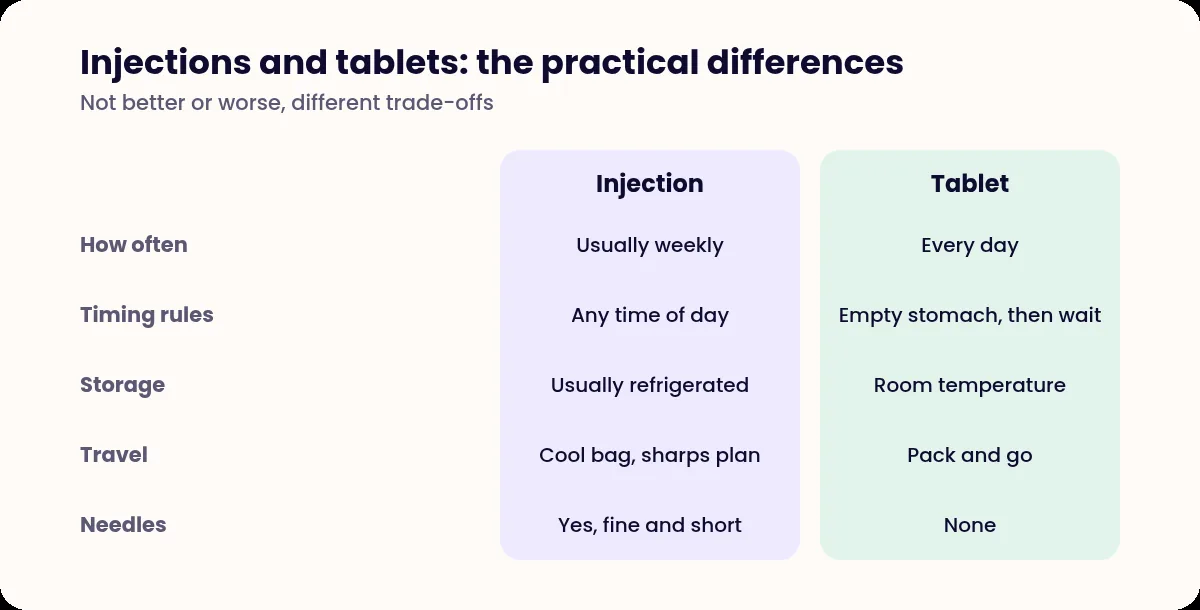
The practical differences
Frequency. A weekly injection is 52 decisions a year. A daily tablet is 365. Neither is obviously better; it depends which kind of routine you actually keep.
Conditions of use. This is where the two tablets diverge sharply. Orforglipron is taken once daily with no food or water restrictions [1]. Oral semaglutide must be taken on an empty stomach after at least eight hours without food, with a sip of water, and nothing else for thirty minutes [2]. If your mornings are chaotic, that difference matters more than any trial result.
Needles. For some people the injection is the barrier and the tablet solves it. For others, one injection a week they barely think about beats a daily ritual.
Dose escalation. All of the GLP-1 based medicines step up gradually over months, because gastrointestinal side effects cluster around dose increases. None of them reaches its maintenance dose quickly.
What the trials found
These figures come from separate trials, in different populations, over different durations. They are not head-to-head comparisons and should not be read as a ranking.
| Medicine and dose | Trial | Average weight change |
|---|---|---|
| Tirzepatide 15 mg weekly | SURMOUNT-1, 72 weeks | about −20% |
| Semaglutide 7.2 mg weekly | STEP UP, 72 weeks | −18.7% |
| Semaglutide 2.4 mg weekly | STEP 1 / STEP UP | about −15% |
| Oral semaglutide 25 mg daily | OASIS-4, 64 weeks | about −14% |
| Orforglipron 36 mg daily | ATTAIN-1, 72 weeks | about −12.4% |
| Liraglutide 3 mg daily | SCALE, 56 weeks | −8.0% |
| Orlistat 120 mg | XENDOS, 4 years | −5.8 kg |
Two things are worth noticing. The newer the medicine, the larger the average — which reflects genuine pharmacological progress, not just marketing. And the gap between the best and the worst is smaller than the gap between someone who stays on treatment and someone who stops.
Orlistat: the different one
Orlistat is not a GLP-1 medicine and does not work on appetite. It inhibits the enzyme that breaks down dietary fat, so roughly a third of the fat you eat passes through undigested [6]. The 120 mg version is prescription-only; a 60 mg version can be supplied by a pharmacist.
Its side effects follow directly from the mechanism: oily stools, urgency, flatulence with discharge — and they are worse the more fat you eat, which is either a drawback or a behavioural feedback loop depending on your point of view. In the four-year XENDOS trial it produced 5.8 kg of weight loss against 3.0 kg on placebo, and reduced progression to type 2 diabetes.
It is cheaper than everything else on this list and remains a legitimate option.
What none of this tells you
NHS availability is a separate question. Neither of the two tablets is currently available on the NHS; NICE evaluations are in progress. NHS access to the injections is governed by NICE technology appraisals and is narrower than the terms of the licences [7].
Averages are not predictions. In every one of these trials, some participants lost a great deal and some lost almost nothing.
Suitability is clinical. Whether any of these is appropriate depends on your BMI, your health history, other medicines you take, and whether you can be monitored properly.
Where this information comes from
Licensing details are from MHRA announcements and the products’ Summaries of Product Characteristics; trial figures from the published phase 3 results. All of this changes — the SmPC on the electronic Medicines Compendium is the current authority on any product’s licensed use.
Frequently asked questions
Which weight loss medicines are licensed in the UK?
For weight management: tirzepatide and semaglutide as weekly injections, semaglutide as a daily 25 mg tablet, orforglipron as a daily tablet, liraglutide as a daily injection, and orlistat as a capsule taken with meals. All are prescription-only except lower-dose orlistat, which a pharmacist can supply.
Are tablets less effective than injections?
The trial averages published so far are lower for the oral options than for the highest-dose injections, but those trials involved different people, different durations and different comparators. They cannot be read as a league table, and the best result is the one a person can actually keep taking.
Which has fewer side effects?
The side-effect profile is broadly similar across the GLP-1 based medicines — mostly gastrointestinal, mostly early, mostly settling. Orlistat is different: its side effects relate to unabsorbed fat passing through the gut.
Is a tablet easier?
It depends which tablet. Orforglipron has no food or water restrictions. Oral semaglutide requires an eight-hour fast, a sip of water, and nothing else for thirty minutes. Some people find a weekly injection simpler than a daily routine of either kind.
Can I choose which one I get?
You can discuss preferences, but which medicine is appropriate — if any is — is a clinical decision based on your health history, other medicines, and what is licensed for your circumstances.
References
- MHRA. UK first in Europe to authorise orforglipron for weight management and type 2 diabetes. 10 August 2026. www.gov.uk/government/news/uk-first-in-europe-to-authorise-orforglipro
- MHRA. First GLP-1 tablet for weight loss approved in the UK. 11 June 2026. www.gov.uk/government/news/first-glp-1-tablet-for-weight-loss-approved
- Eli Lilly and Company Limited. Mounjaro KwikPen: Summary of Product Characteristics. Electronic Medicines Compendium. www.medicines.org.uk/emc/product/15484/smpc
- Novo Nordisk Limited. Wegovy: Summary of Product Characteristics. Electronic Medicines Compendium. www.medicines.org.uk/emc/product/13803/smpc
- Novo Nordisk Limited. Saxenda (liraglutide): Summary of Product Characteristics. Electronic Medicines Compendium. www.medicines.org.uk/emc/product/2313/smpc
- NHS. Orlistat. Page last reviewed 6 May 2026. www.nhs.uk/medicines/orlistat/
- National Institute for Health and Care Excellence. Semaglutide for managing overweight and obesity (TA875). www.nice.org.uk/guidance/ta875/chapter/1-Recommendations
Medical reviewer
Naeem Teni
Clinical Lead at Manova. Registered pharmacist and independent prescriber, GPhC 2215591. Reviews Manova’s clinical content for accuracy and safety.
Written by
Manova Editorial Team
Researched and written to our editorial policy, using NICE, NHS, MHRA and peer-reviewed sources.
This article is for general information and isn’t a substitute for advice from your own clinician. If you feel unwell, contact your GP or NHS 111. In an emergency, call 999.