
Key takeaways
- Tadalafil has a 17.5 hour half-life and showed effect up to 36 hours; sildenafil's half-life is 3–5 hours.
- Tadalafil absorption is unaffected by food; sildenafil's onset is delayed by a meal.
- Only tadalafil is licensed for once-daily use and for benign prostatic hyperplasia.
- Their cardiovascular contraindications are not identical and should not be assumed to be.
Both are PDE5 inhibitors and both work by the same mechanism. The differences that matter in practice are about timing, food and what each is licensed for. This is information about prescription medicines, not a recommendation.
The comparison
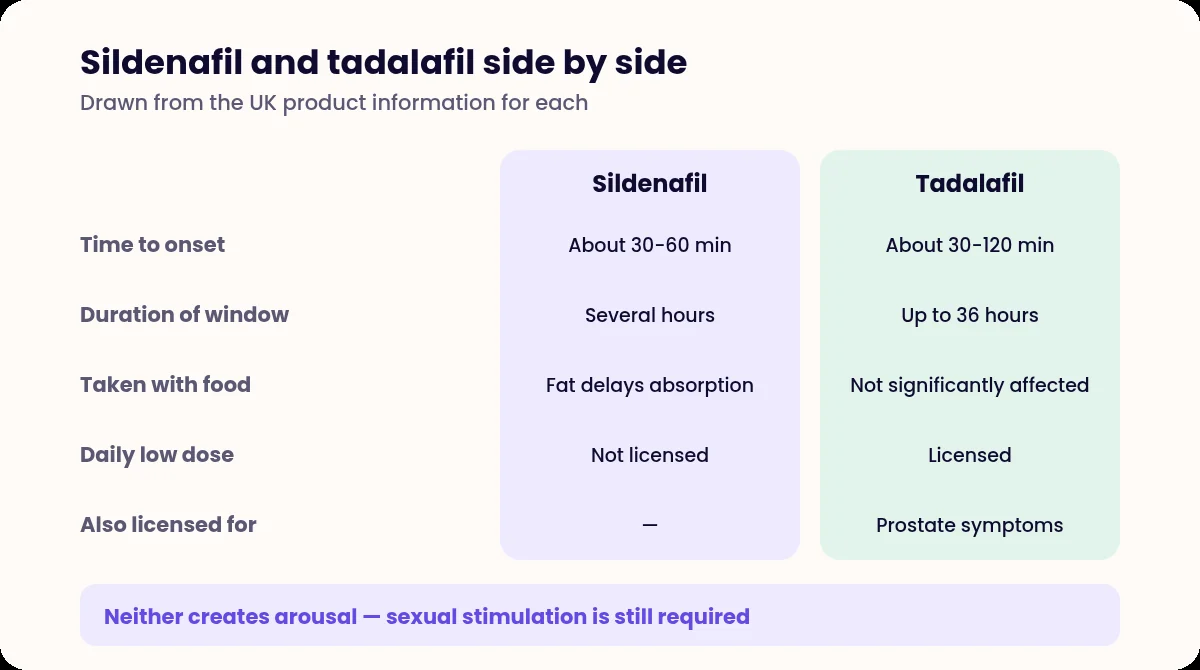
| Sildenafil | Tadalafil | |
|---|---|---|
| Licensed doses | 25, 50, 100 mg | 2.5, 5, 10, 20 mg |
| Usual starting dose | 50 mg as needed | 10 mg as needed, or 5 mg once daily |
| Maximum frequency | once per day | once per day |
| Take before activity | about 1 hour | at least 30 minutes |
| Time to peak level | 30–120 minutes (median 60) | median 2 hours |
| Half-life | 3–5 hours | 17.5 hours |
| Duration in product information | not stated | up to 36 hours |
| Effect of food | onset may be delayed | not influenced |
| Licensed for daily use | no | yes (2.5 / 5 mg) |
| Licensed for enlarged prostate | no | yes (5 mg) |
Sources: the UK Summaries of Product Characteristics [1][2].
What each difference means in practice
Duration
Tadalafil’s product information records statistically significant improvement in erectile function and the ability to have successful intercourse up to 36 hours after dosing, with effect as early as 16 minutes [2].
Sildenafil’s product information does not state a duration of effect at all — it gives a half-life of 3–5 hours and a time to peak of 30–120 minutes [1]. The widely quoted “4 to 6 hours” is a clinical convention rather than licensed information, which is worth knowing if you have been told it as fact.
The practical consequence is about spontaneity. A longer window removes the need to time a dose to an occasion.
Food
This one is underrated. Tadalafil’s absorption is not influenced by food. Sildenafil’s onset may be delayed when taken with a meal, particularly a high-fat one.
A meaningful share of “it didn’t work” experiences with sildenafil are a dose taken after dinner.
Daily dosing
Only tadalafil has a licensed once-daily regimen — 5 mg, reducible to 2.5 mg on tolerability — intended for men anticipating frequent use, generally taken as at least twice weekly [2]. The product information notes that continued use of the daily regimen should be reassessed periodically.
Sildenafil has no daily licence.
Enlarged prostate
Tadalafil 5 mg once daily is licensed for the signs and symptoms of benign prostatic hyperplasia, and the same 5 mg dose covers men who have both conditions [2]. Its product information specifically notes that 2.5 mg is not adequate for BPH.
Sildenafil, vardenafil and avanafil have no UK BPH licence. This is a genuine clinical difference rather than a marketing one.
Contraindications are not identical
A frequent and consequential error is assuming the cardiovascular limits transfer between the two:
- Sildenafil: contraindicated with a “recent history” of stroke or myocardial infarction — no interval is specified in the product information [1]
- Tadalafil: contraindicated with myocardial infarction within the last 90 days, stroke within the last 6 months, NYHA class II or greater heart failure in the last 6 months, uncontrolled arrhythmias, blood pressure below 90/50, or uncontrolled hypertension [2]
Both are absolutely contraindicated with nitrates in any form — including GTN, isosorbide, nicorandil, molsidomine and amyl nitrite (“poppers”) — and with riociguat, and in anyone who has lost vision in one eye from NAION.
Alpha blockers are a precaution rather than a contraindication for both, with the specific note that tadalafil plus doxazosin is not recommended [2].
Side effects
Broadly similar: headache, flushing, indigestion, nasal congestion, back and muscle aches. Back and muscle ache is reported somewhat more with tadalafil; visual disturbance somewhat more with sildenafil.
Current tadalafil labelling notes that observational data suggest an increased risk of acute NAION in men with erectile dysfunction exposed to PDE5 inhibitors, and names central serous chorioretinopathy, most cases of which resolved after stopping [2].
Urgent attention is needed for an erection lasting more than four hours, sudden vision loss, or sudden hearing loss. Suspected side effects can be reported through the Yellow Card scheme [4].
Which suits whom
That is a prescriber’s judgement, based on your cardiovascular history, other medicines, how often you anticipate use, whether you also have urinary symptoms, and how you respond.
What is reasonable to bring to that conversation: how often you expect to need it, whether planning around meals is a problem, and whether you have prostate symptoms as well.
Safety information
Both are prescription-only medicines in the UK. They require a consultation covering cardiovascular history, current medicines and other conditions. Do not obtain them from sellers that do not require one.
When to speak to a clinician
Seek advice before use if you:
- take nitrates in any form, including GTN spray, nicorandil or poppers, or take riociguat
- have had a recent heart attack or stroke, unstable angina, or heart failure
- have uncontrolled blood pressure in either direction
- have significant liver or kidney impairment
- have a retinal disorder, or have lost vision in one eye from NAION
- have sickle cell disease, myeloma or leukaemia
- get chest pain or severe breathlessness walking briskly for 20 minutes or climbing two flights of stairs
Attend A&E for an erection lasting more than four hours, or sudden loss of vision or hearing.
Frequently asked questions
What is the main difference between sildenafil and tadalafil?
Duration. Tadalafil has a half-life of 17.5 hours and its product information records improvement in erectile function up to 36 hours after a dose. Sildenafil has a half-life of 3 to 5 hours.
Does food affect them differently?
Yes, and this is a practical difference. Tadalafil absorption is not influenced by food. Sildenafil's onset may be delayed if taken with a meal, particularly a high-fat one.
Can either be taken daily?
Only tadalafil is licensed for a once-daily regimen, at 2.5 or 5 mg, intended for men anticipating frequent use. Sildenafil is licensed for use as needed, at a maximum of once per day.
Is one stronger than the other?
They are not directly comparable by dose, and UK advertising rules prohibit superlative claims about prescription medicines in any case. They have different dose ranges, different time profiles and different licensed indications.
References
- Viagra (sildenafil) Summary of Product Characteristics. Revised December 2025. www.medicines.org.uk/emc/product/7978/smpc
- Cialis (tadalafil) Summary of Product Characteristics. Revised 27 January 2026. www.medicines.org.uk/emc/product/7432/smpc
- British Society for Sexual Medicine. Guidelines on the management of erectile dysfunction in men. 2018. bssm.org.uk/wp-content/uploads/2023/02/BSSM-ED-guidelines-2018-1.pdf
- MHRA. Yellow Card: report a suspected side effect. yellowcard.mhra.gov.uk/
Medical reviewer
Naeem Teni
Clinical Lead at Manova. Registered pharmacist and independent prescriber, GPhC 2215591. Reviews Manova’s clinical content for accuracy and safety.
Written by
Manova Editorial Team
Researched and written to our editorial policy, using NICE, NHS, MHRA and peer-reviewed sources.
This article is for general information and isn’t a substitute for advice from your own clinician. If you feel unwell, contact your GP or NHS 111. In an emergency, call 999.