

Key takeaways
- NICE defines low-energy diets as 800–1,200 kcal/day and very-low-energy diets as under 800.
- Very-low-energy diets should be used only within a specialist service, and only where rapid loss is clinically needed.
- Maximum 12 weeks, nutritionally complete, with dietitian access.
- Risks NICE asks to be explained include weight cycling, likely regain, constipation, fatigue and hair loss.
Eating under 800 calories a day is not an aggressive diet. In UK guidance it is a clinical intervention with defined indications, a maximum duration and required supervision — closer to a short course of treatment than to a lifestyle choice.
Understanding why makes the rules seem less arbitrary.
The definitions
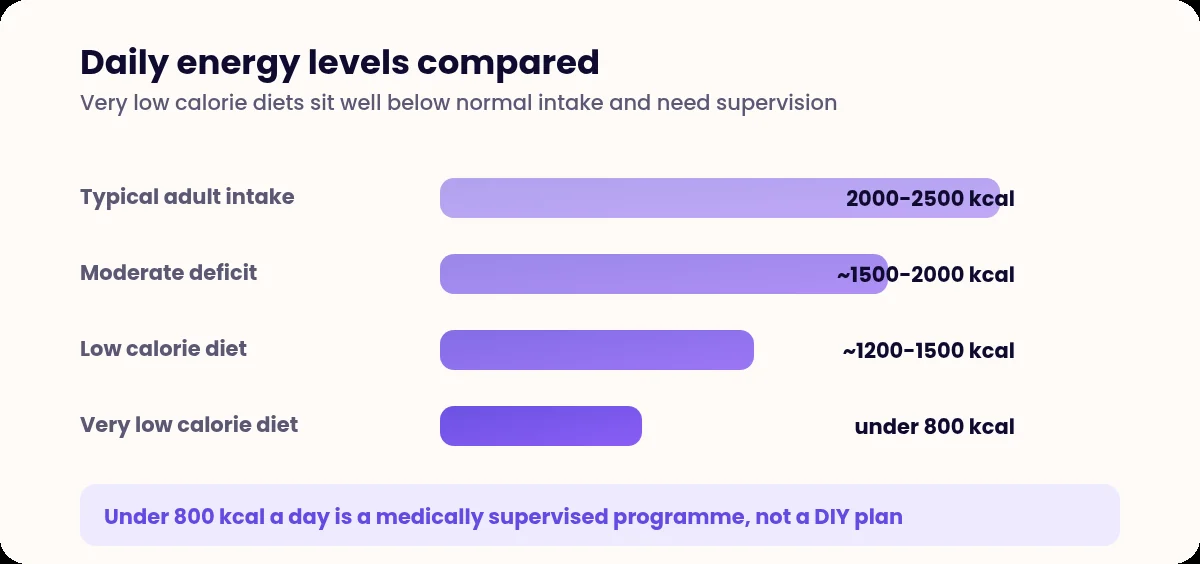
NICE uses two terms [1]:
| Term | Intake | Also called |
|---|---|---|
| Low-energy diet | 800–1,200 kcal/day | Low-calorie diet |
| Very-low-energy diet | Under 800 kcal/day | Very-low-calorie diet |
Both are normally delivered as total or partial meal replacement, because hitting those intakes with ordinary food while remaining nutritionally complete is close to impossible.
What NICE permits
The recommendations are unusually prescriptive [1]:
Low-energy diets (800–1,200 kcal) — consider only as part of a multicomponent strategy with long-term support, within a specialist overweight and obesity management service or another long-term condition service, for people living with obesity, or with overweight and type 2 diabetes.
Very-low-energy diets (under 800 kcal) — consider only within a specialist service, for people living with obesity who have a clinically assessed need to lose weight rapidly — for example to make surgery safer or possible.
Neither should be used as a long-term strategy.
Both must be nutritionally complete, last no more than 12 weeks, and include ongoing clinical supervision with access to a registered dietitian or nutritionist, plus advice on reintroducing a wider range of foods.
The risks NICE asks to be explained
Before starting, guidance says the following must be discussed [1]:
- Weight cycling and weight regain — and that regain is likely, and is not a personal failure
- That this is not a standalone long-term strategy
- For very-low-energy diets specifically: constipation, fatigue and hair loss
- An assessment and counselling offer for possible eating disorders or other mental health issues
- A review of all medicines
That last item is the one most likely to matter medically. Blood pressure medicines, diabetes medicines — particularly insulin and sulfonylureas — and some others need dose changes as intake drops, sometimes within days.
The hair loss point deserves its own mention, because it surprises people badly. Rapid weight loss commonly triggers telogen effluvium, which starts around three months after the trigger and is self-limiting. We cover it in hair loss after weight loss.
Other risks worth knowing
Gallstones. Rapid weight loss increases the risk of gallstone formation, sometimes requiring surgery.
Gout. Rapid loss can precipitate an attack in susceptible people.
Muscle loss. Expected with rapid loss; reduced but not eliminated by adequate protein and resistance training.
Cold, tiredness, poor concentration. Common and usually tolerable, but a real consideration if you drive for a living or operate machinery.
Where they genuinely shine
Type 2 diabetes. The DiRECT trial used total diet replacement and produced 46% remission at 12 months. At five years, remission had fallen to about 13% in the extension group against 5% in controls — durability is much lower than the headline [3].
The NHS has built a national programme on this. The Type 2 Diabetes Path to Remission Programme provides 12 weeks of total diet replacement at 800–900 kcal, structured reintroduction, and a year of support, free, for adults aged 18–65 with type 2 diabetes diagnosed in the last six years [2].
If you have type 2 diabetes and are considering an 800 calorie diet, ask your GP about that programme before buying anything. It is the supervised version, and it is free.
If you are going to do it anyway
Some people will, and pretending otherwise helps nobody.
- Use a nutritionally complete product designed for the purpose, not a homemade 800 calorie plan
- Tell your GP, specifically so medicines can be reviewed
- Drink plenty and address constipation early
- Keep protein at the upper end of what the product provides, and do resistance work twice a week
- Set an end date — 12 weeks maximum — and write the reintroduction plan before you start
- Stop and seek advice for chest pain, palpitations, fainting, severe abdominal pain, or persistent vomiting
When to speak to a clinician
Speak to a clinician before starting, and urgently if problems arise, if you:
- take insulin, a sulfonylurea, or blood pressure medicines
- have type 1 diabetes — these diets are not appropriate
- are pregnant or breastfeeding
- have a history of an eating disorder
- have gallstones, gout, kidney or liver disease, or a history of cardiac arrhythmia
- develop severe upper abdominal pain, fainting, palpitations or persistent vomiting while on one
Frequently asked questions
What counts as a very low calorie diet?
In NICE terminology, a very-low-energy diet is under 800 kcal a day. A low-energy diet is 800 to 1,200 kcal a day. Both are meant to be nutritionally complete and time-limited.
Can I do an 800 calorie diet on my own?
NICE restricts both low- and very-low-energy diets to structured programmes with long-term support, and very-low-energy diets to specialist services. Doing it unsupervised carries risks around medication doses, nutritional adequacy and gallstones, and there is no follow-on plan when it ends.
How long can you stay on one?
No more than 12 weeks, according to NICE, and they should not be used as a long-term strategy at all. The intervention is the 12 weeks plus the structured reintroduction and support that follow.
Do you lose muscle on a very low calorie diet?
Some lean tissue loss is expected with any rapid weight loss. Adequate protein and resistance training reduce it. This is one reason these diets are time-limited and supervised rather than open-ended.
References
- NICE. Overweight and obesity management. NG246. January 2025. www.nice.org.uk/guidance/ng246
- NHS England. Type 2 Diabetes Path to Remission Programme. www.england.nhs.uk/diabetes/treatment-care/diabetes-remission/
- Lean MEJ, Leslie WS, Barnes AC, et al. Durability of a primary care-led weight management intervention for remission of type 2 diabetes: 5-year results of the DiRECT open-label, cluster-randomised trial. The Lancet Diabetes & Endocrinology. 2024;12(4):233-246. doi.org/10.1016/S2213-8587(23)00385-6
- NHS. Gallstones. www.nhs.uk/conditions/gallstones/
Medical reviewer
Naeem Teni
Clinical Lead at Manova. Registered pharmacist and independent prescriber, GPhC 2215591. Reviews Manova’s clinical content for accuracy and safety.
Written by
Manova Editorial Team
Researched and written to our editorial policy, using NICE, NHS, MHRA and peer-reviewed sources.
This article is for general information and isn’t a substitute for advice from your own clinician. If you feel unwell, contact your GP or NHS 111. In an emergency, call 999.