
Key takeaways
- All four PDE5 inhibitors work the same way; the meaningful differences are onset, duration, food effects and cost.
- Avanafil has the fastest onset at 15 to 30 minutes; tadalafil has by far the longest duration at up to 36 hours.
- Since 1 October 2025, generically written tadalafil and vardenafil no longer need SLS endorsement for NHS prescribing — a significant widening of access most published content still gets wrong.
- No head-to-head randomised trials compare avanafil with the others, so every comparative claim about it is indirect.
This page is medicine information rather than an advert. Vardenafil and avanafil are prescription only medicines in the UK, and whether either is suitable is a decision for a prescriber after an assessment.
Four PDE5 inhibitors are licensed and marketed in the UK: sildenafil, tadalafil, vardenafil and avanafil. They share a mechanism, described in our guide to how PDE5 inhibitors work, and the differences between them are narrower than marketing in other countries suggests. What differs is timing.
The comparison that matters
European guidance sets the four out side by side [1]:
| Sildenafil 100 mg | Tadalafil 20 mg | Vardenafil 20 mg | Avanafil 200 mg | |
|---|---|---|---|---|
| Onset | 30–60 min | 30 min (peak ~2 h) | 30 min | 15–30 min |
| Duration | up to 12 h | up to 36 h | ~8–10 h | 6–17 h |
| Half-life | 2.6–3.7 h | 17.5 h | 3.9 h | 6–17 h |
| Food effect | delayed by high-fat meal | minimal or none | delayed by high-fat meal | delayed by high-fat meal |
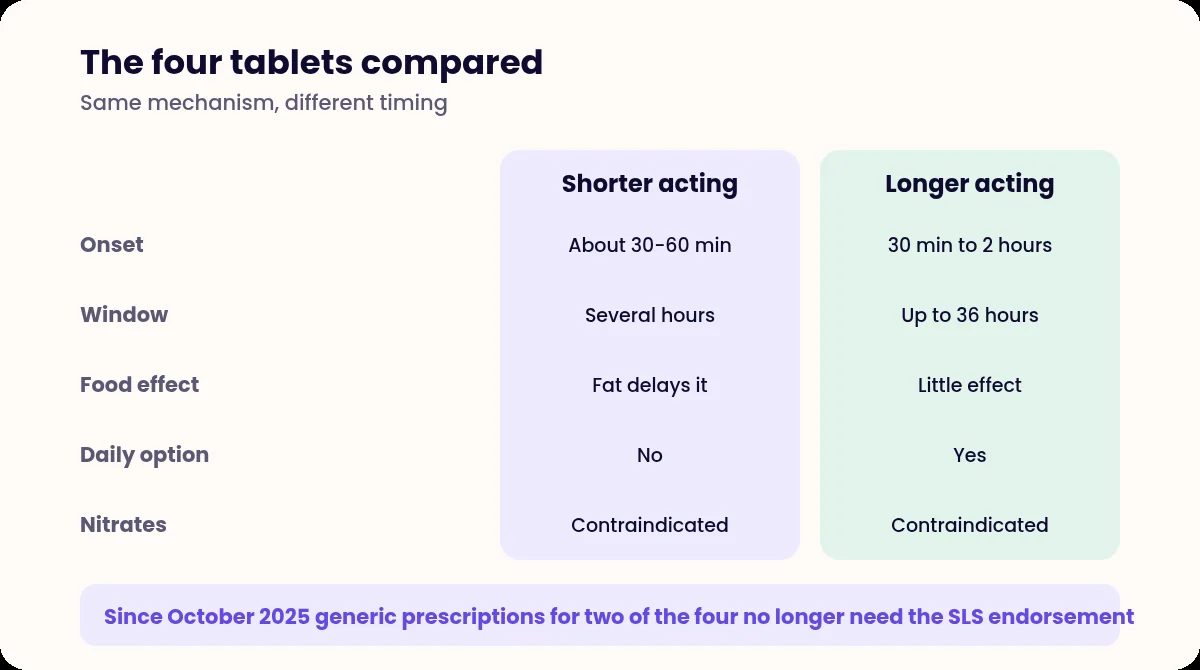
Read down the columns and the practical picture emerges. Tadalafil is the outlier on duration and the only one that is essentially unaffected by food. Avanafil is the outlier on speed. Sildenafil and vardenafil sit close together in the middle.
Vardenafil
Vardenafil is best understood as a close analogue of sildenafil. Onset and duration are broadly similar. It is somewhat more potent per milligram, which is why the strengths are 5, 10 and 20 mg rather than 25, 50 and 100 mg. A high-fat meal delays it in the same way.
Two specifics are worth knowing. An orodispersible 10 mg form is licensed, which dissolves on the tongue without water; the product information advises against taking it with food. And vardenafil carries a modest additional caution around QT interval prolongation compared with the others, which matters for men on certain antiarrhythmic medicines or with a known long QT syndrome [3].
For a man who has had an inadequate response to sildenafil, vardenafil is a reasonable switch, though the two are pharmacologically close enough that a change to tadalafil often represents a bigger change in the variable that was the problem.
Avanafil
Avanafil, marketed as Spedra in 50, 100 and 200 mg strengths, is the newest of the four and the fastest. It can be taken 15 to 30 minutes before sex, which is a genuinely different proposition from planning an hour ahead.
It is also more selective for PDE5 than the older molecules, which translates into lower reported rates of flushing and visual disturbance — the visual effects in particular come from crossover onto a related enzyme in the retina, and greater selectivity means less of it.
The important caveat: there are no head-to-head randomised trials comparing avanafil with sildenafil, tadalafil or vardenafil [1]. Every comparative statement about it, including the ones above, is an indirect comparison between separate placebo-controlled trials. That is a weaker form of evidence than it sounds when the numbers are printed in a table.
What is actually prescribed in the UK
Real-world UK prescribing is dominated by generic sildenafil and generic tadalafil. They are the cheapest, the most familiar, and now the least restricted. Vardenafil and avanafil are prescribed in far smaller volumes and are more often private or specialist.
This is a genuine UK–US difference. Avanafil has a substantially larger market presence in the United States, where it is marketed as Stendra, and US-written content tends to treat it as a mainstream option. UK uptake is small.
There have been claims circulating in 2026 about an avanafil supply problem. These do not appear in authoritative sources, and the place to check is the NHS Specialist Pharmacy Service medicines supply tool rather than a forum [6].
The October 2025 SLS change
This is the most consequential recent change to UK ED prescribing, and most published content — including content updated since — still describes the old position.
NHS prescribing of erectile dysfunction treatments has historically been restricted by the Selected List Scheme, which requires a prescription to be endorsed “SLS” and limits NHS supply to men meeting specific clinical criteria. Generic sildenafil came out of that restriction in 2014.
From 1 October 2025, the SLS endorsement requirement was removed for generically written tadalafil and vardenafil [2]. In practical terms, a generic prescription for either can now be written on the NHS without the endorsement and without the man needing to meet an SLS qualifying condition.
What still requires SLS endorsement:
- Branded Viagra, Cialis and Levitra.
- Avanafil (Spedra).
- Alprostadil products and vacuum devices.
The effect is that two of the four PDE5 inhibitors, including the long-acting one, are now straightforwardly NHS-prescribable where clinically appropriate — a much wider position than a year ago. Our guide to NHS options for erectile dysfunction sets out the remaining criteria and how they apply.
There is no US equivalent to the SLS. US access is governed by insurance formularies instead, which is why American comparisons of these four medicines never mention it.
Contraindications, which are the same for all four
Nitrates in any form, and nicorandil, are absolutely contraindicated with every PDE5 inhibitor. The combination can cause a profound and potentially fatal fall in blood pressure. Riociguat is likewise excluded. Alpha blockers require care rather than absolute avoidance, and the specifics matter — our guide to blood pressure medicines and erections covers that territory.
Because tadalafil has a 17.5-hour half-life, the washout period before a nitrate can be given is longer for tadalafil than for the other three. Anyone carrying a GTN spray must say so before any of these is prescribed.
How to choose between them
The honest answer is that the molecule usually matters less than dose, timing and whether the trial was long enough. Where the choice does turn on something real:
- Wanting a long window rather than planning around a tablet points to tadalafil.
- Wanting the shortest possible lead time points to avanafil.
- Meals and alcohol being a regular part of the evening points away from sildenafil, vardenafil and avanafil.
- Flushing or visual effects that were troublesome on an older molecule point towards the more selective one.
Our sildenafil versus tadalafil comparison covers the two that most men will actually be offered.
Frequently asked questions
Which PDE5 inhibitor works fastest?
Avanafil, at 15 to 30 minutes, against 30 to 60 minutes for sildenafil and around 30 minutes for tadalafil and vardenafil. That difference is real in the pharmacology, but there are no head-to-head randomised trials, so comparisons between the four are indirect rather than directly measured.
Is vardenafil different from sildenafil in practice?
Only modestly. Onset and duration are broadly similar, vardenafil is somewhat more potent per milligram, which is why its strengths are 5, 10 and 20 mg, and it carries slightly more caution around QT interval. An orodispersible 10 mg form is also licensed, which should not be taken with food.
Did the NHS rules on tadalafil change?
Yes. From 1 October 2025 the Selected List Scheme endorsement requirement was removed for generically written tadalafil and vardenafil, so a generic prescription no longer needs the SLS endorsement. Branded Cialis and Levitra still require it, as does avanafil. Generic sildenafil has been unrestricted since 2014.
Does food affect these tablets?
Sildenafil, vardenafil and avanafil are all delayed by a high-fat meal. Tadalafil is the exception, with minimal or no food effect. This is one of the more practically useful differences and a common reason a tablet appears not to have worked.
References
- European Association of Urology. Guidelines on Sexual and Reproductive Health: Management of Erectile Dysfunction. uroweb.org/guidelines/sexual-and-reproductive-health/chapter/managemen
- Community Pharmacy England. Revisions to SLS list for October 2025. cpe.org.uk/our-news/revisions-to-sls-list-for-october-2025/
- British National Formulary. Erectile dysfunction: drug treatment. bnf.nice.org.uk/treatment-summaries/erectile-dysfunction/
- Summary of Product Characteristics: Spedra (avanafil) tablets. Electronic Medicines Compendium. www.medicines.org.uk/emc/
- British Society for Sexual Medicine. Guidelines on the management of erectile dysfunction in men (2018). bssm.org.uk/wp-content/uploads/2023/02/BSSM-ED-guidelines-2018-1.pdf
- Specialist Pharmacy Service. Medicines supply tool. sps.nhs.uk/category/medicines-tools/medicines-supply/
Medical reviewer
Naeem Teni
Clinical Lead at Manova. Registered pharmacist and independent prescriber, GPhC 2215591. Reviews Manova’s clinical content for accuracy and safety.
Written by
Manova Editorial Team
Researched and written to our editorial policy, using NICE, NHS, MHRA and peer-reviewed sources.
This article is for general information and isn’t a substitute for advice from your own clinician. If you feel unwell, contact your GP or NHS 111. In an emergency, call 999.